The right ultrasound depends on how many weeks pregnant you are, what your obstetrician needs to assess, and whether you have symptoms that require urgent care. By the end, you will know when common scans are performed, how to prepare, what the report means, and how to arrange the correct examination.
Key takeaways
- Routine scans answer different questions at different pregnancy stages.
- Ask how to prepare before booking, including whether you need a full bladder.
- An ultrasound report describes findings; it cannot guarantee a healthy baby.
- Seek urgent help for heavy bleeding, severe pain, or reduced fetal movement.
Which routine pregnancy scan is needed at each stage?
A routine schedule uses scans for different questions at different stages; not every pregnancy needs every scan.
| Scan | Main purpose | Usual timing |
|---|---|---|
| Dating scan | Estimate gestational age, especially with uncertain dates; confirm location and number of fetuses | 7–13 weeks |
| Viability scan | Confirm an intrauterine pregnancy, heartbeat and expected development | Early pregnancy, when symptoms or dates require it |
| Nuchal translucency scan | Measure the fluid behind the fetal neck as part of first-trimester screening | 11 weeks 0 days to 13 weeks 6 days, with CRL 45–84 mm |
| Anatomy or level-II scan | Examine the brain, spine, heart, abdomen, limbs, face, placenta and amniotic fluid | 18–22 weeks |
| Growth scan | Measure fetal growth, fluid and placental function when monitoring is indicated | Commonly after 28 weeks, according to need |
| Fetal wellbeing assessment | Assess movement, fluid, growth and selected blood-flow findings | Later pregnancy when symptoms or risk factors justify it |
| Position scan | Check fetal presentation and placental location before birth planning | Late pregnancy |
A first-trimester ultrasound is particularly useful after assisted conception because dates are known from treatment, and in twin pregnancy it should document chorionicity and amnionicity—the number of placentas and amniotic sacs. Monochorionic twins need closer surveillance because complications such as twin-to-twin transfusion syndrome differ from dichorionic twins.
Your clinician may add, move or repeat scans for bleeding, pain, reduced movements, uncertain dates, fetal measurements, placental concerns or a high-risk pregnancy. Know the difference between routine versus urgent assessment: a scheduled scan cannot replace immediate care for heavy bleeding, severe pain or reduced fetal movement.
What happens during the appointment, and how should you prepare?
At registration, bring your referral, identification, last menstrual period, estimated due date, and prior reports or images. Wear two-piece clothing so you can expose your abdomen without changing completely. There is no routine fasting for pregnancy ultrasound.
Follow the centre’s bladder instructions: an early abdominal scan may require a comfortably full bladder, while an internal scan requires an empty bladder. Ask whether a support person may attend.
| Method | What happens | Bladder |
|---|---|---|
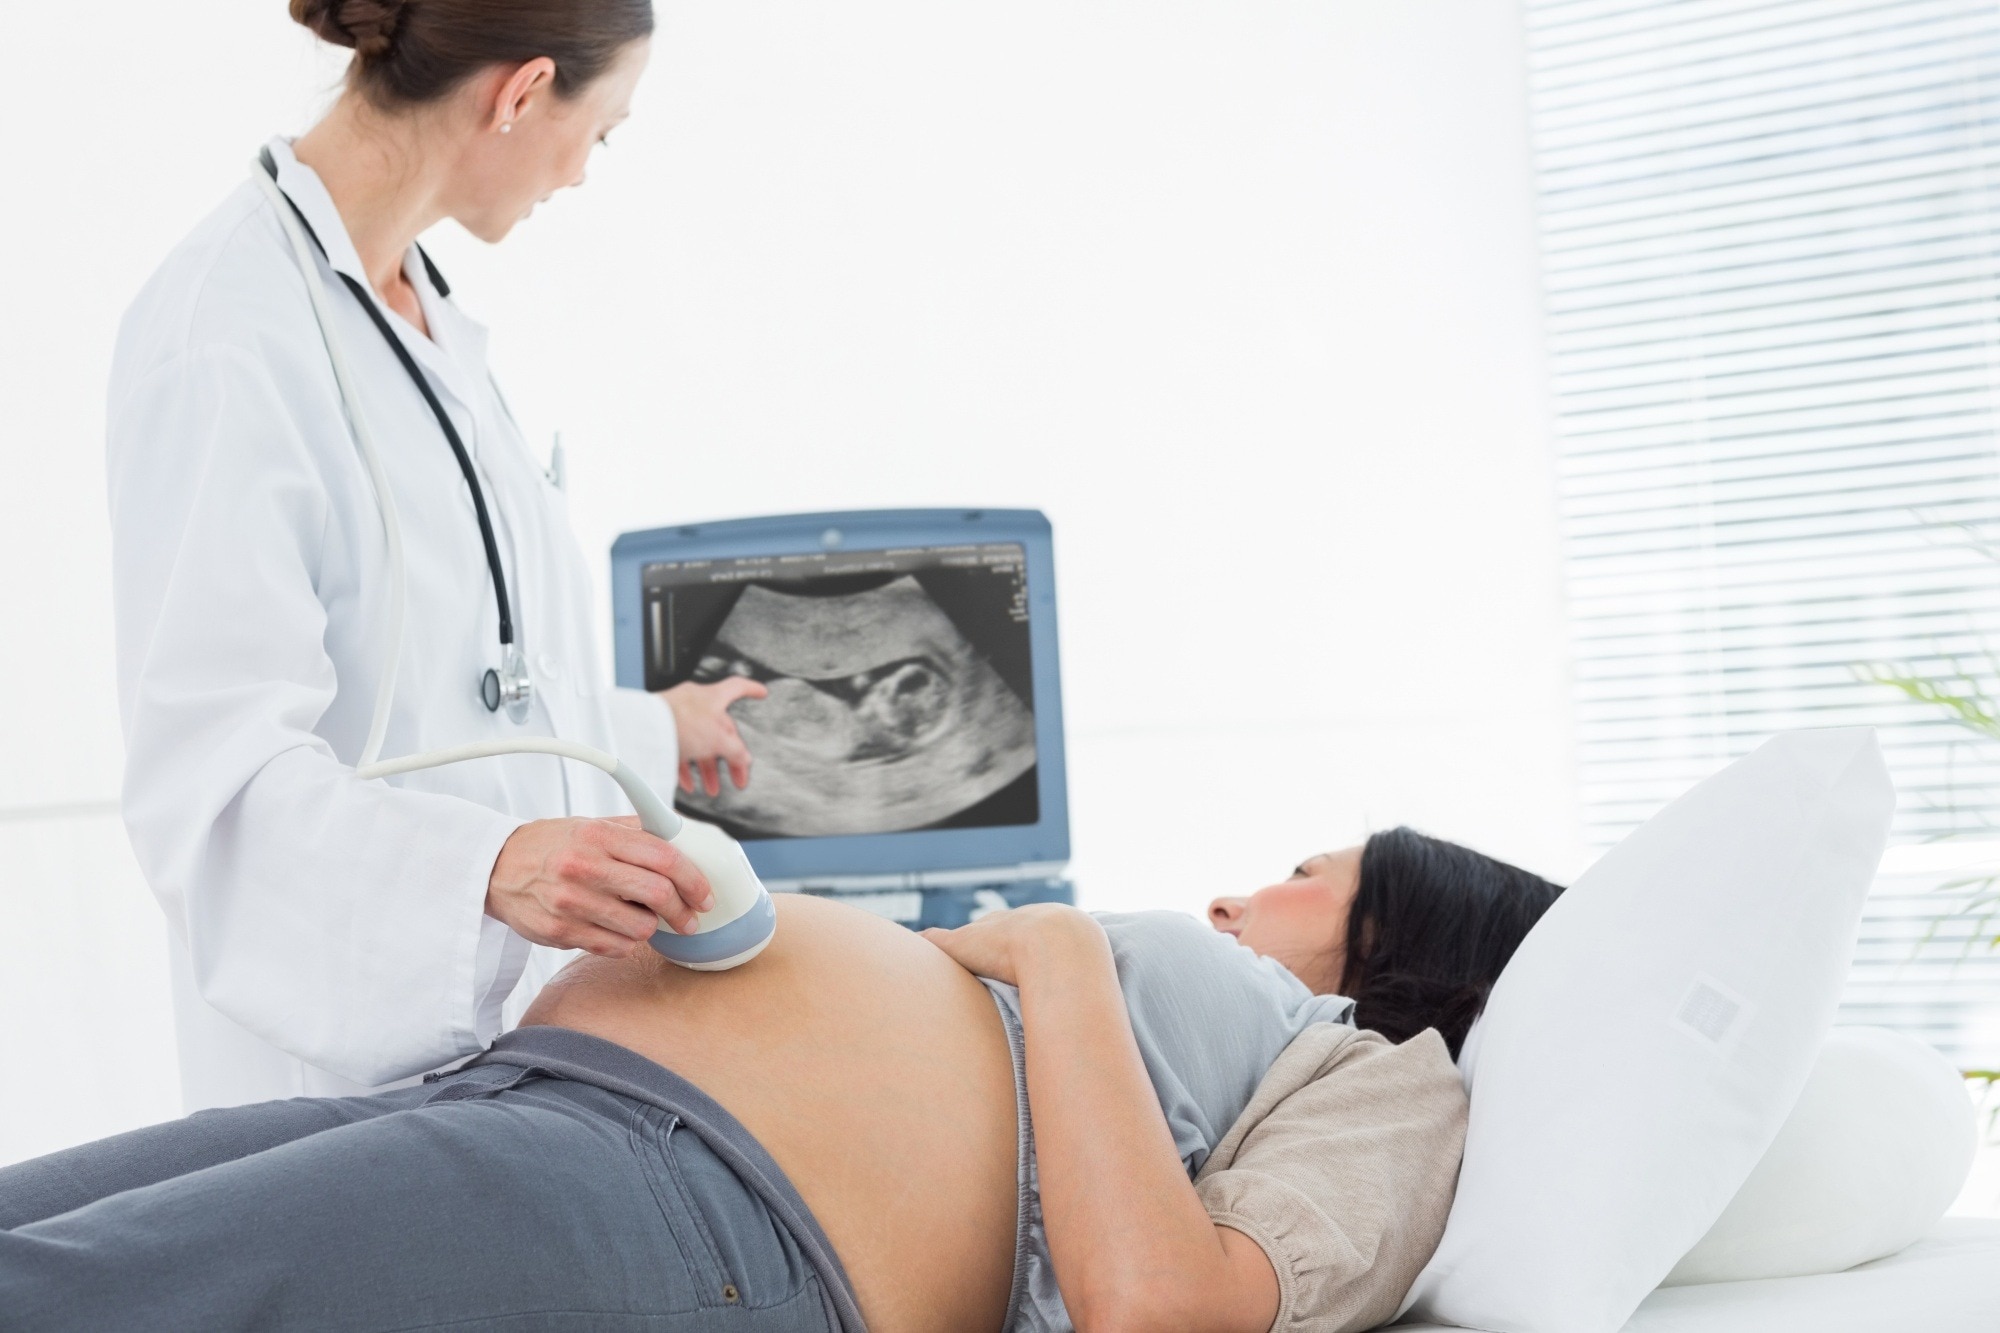
| Transabdominal ultrasound | You lie on your back while the sonographer applies cool gel and moves a probe over your abdomen. You may feel probe pressure, but the scan should not be painful. | A comfortably full bladder may improve early pelvic views; follow the centre’s instructions. |
| Transvaginal ultrasound | You remove clothing from the waist down and a covered, lubricated probe enters the vagina. It provides clearer early images because it sits closer to the uterus; expect pressure rather than sharp pain. | Empty bladder |
Scan duration depends on the examination, gestational age, and image quality. Fetal position, movement, body tissues, or limited visibility can leave incomplete views, especially during the anatomy scan. The sonographer may ask you to change position or walk briefly.
A repeat scan does not automatically mean a problem. It may be needed when fetal position blocks a required view, measurements are incomplete, or growth and wellbeing need review later. Ask when and how you will receive the report.
What will the ultrasound report show, and what can it not prove?
An ultrasound report describes what was visible that day; it does not certify a healthy pregnancy. Early entries may include a gestational sac and fetal heart rate or fetal heart activity (FHR). Crown-rump length (CRL) estimates gestational age, but every value has a measurement margin, so a small difference is not automatically a problem.
| Feature | What it indicates | What it cannot prove |
|---|---|---|
| Biparietal diameter (BPD), head circumference (HC), abdominal circumference (AC), and femur length (FL) | Fetal size and growth pattern | A diagnosis from one measurement |
| Estimated fetal weight (EFW) | A calculated size estimate | The exact birth weight |
| Amniotic fluid index (AFI) | An assessment of fluid volume | A cause for an abnormal result |
| Nuchal translucency (NT) | A first-trimester screening marker | A chromosome diagnosis |
| Placenta, cervix, and fetal presentation | Location, cervical appearance, and position | Whether a low-lying placenta will remain near the cervix |
An echogenic focus or choroid plexus cyst can be an isolated finding, not a diagnosis. Fetal presentation can be breech presentation without predicting the birth position.
Keep screening versus diagnosis separate: NT is commonly interpreted with combined blood tests or cell-free DNA, but neither combination confirms a condition. A size-date discrepancy or concerning view may lead to repeat imaging, a fetal echocardiogram, or diagnostic testing.
A limited study means views were incomplete, not normal; even a normal anatomy scan cannot exclude every defect.
What is normal during a scan, and when should you seek urgent help?
Cool gel, brief pressure, and probe pressure are normal. A transvaginal scan can feel uncomfortable but should not be sharply painful; when performed appropriately, it is not known to increase miscarriage risk.
Ultrasound uses sound waves, not ionizing radiation. Medically indicated diagnostic ultrasound follows the ALARA principle: keep exposure as low as reasonably achievable. Doppler adds blood-flow assessment and is used for a clinical reason by a trained practitioner. A home fetal Doppler cannot reliably confirm fetal wellbeing.
Understand normal scan limitations. A reassuring image cannot exclude every genetic condition, birth defects, autism, small heart defects, or later complications. The standard anomaly scan is not a complete heart examination; risk factors may require fetal echocardiography.
A keepsake scan, including 3D or 4D imaging, cannot replace antenatal care, diagnostic testing, or a medically indicated examination.
Seek urgent report advice from your obstetrician for an unexpected result, but do not wait for a scheduled scan when you have:
- vaginal bleeding
- severe abdominal pain
- fainting
- leaking fluid
- reduced fetal movement
These symptoms need emergency care or your local maternity triage service. A scheduled scan cannot assess a sudden change safely because it may be days away, and an ultrasound appointment does not replace clinical assessment. Contact the maternity unit immediately if you are unsure how urgently to act.
How do you book the correct scan and choose a provider?
Start by naming the examination you need: a pregnancy ultrasound, not a general pelvic ultrasound or routine abdominal ultrasound. Ask whether it is transabdominal, transvaginal, nuchal translucency, anatomy, growth, or Doppler imaging, and give the centre your gestational age and referral.
Provider comparison matters because a scan is only useful when the report reaches the right clinician in time.
| Provider | Confirm before booking | Why it matters |
|---|---|---|
| Radiologist or sonologist | Name, qualifications, and who will interpret the study | You know who is responsible for the findings |
| Centre | Ultrasound equipment, operator name, images, measurements, and report turnaround | You can compare technical quality and timing |
| Communication desk | Urgent findings communication and referring doctor protocol | A concerning result is not left waiting in your inbox |
| Records policy | Report retention, image access, and whether prior measurements can be reviewed | Follow-up depends on comparable records |
Ask whether you receive printed or digital images, the complete report, and instructions for follow-up. Confirm preparation in writing: a full bladder may help an early abdominal scan, while it is usually unnecessary for transvaginal imaging.
Do not assume an Antenatal Screening package includes the scan. At Augmentum Diagnostics, ask whether the package’s blood and urine tests are booked separately from ultrasound, and whether one appointment covers both. If you are comparing centres in Janak Puri or Dwarka, confirm these details before paying.
Frequently asked questions
Which routine pregnancy scans are needed at each stage?
Early pregnancy scans assess location, dating, and heartbeat when indicated. The 11–14-week scan assesses dating and early fetal development, while the 18–22-week anomaly scan examines anatomy. Later scans are recommended when your clinician needs to assess growth, position, placenta, fluid, or wellbeing.
How should you prepare for a pregnancy ultrasound appointment?
Follow the provider’s instructions because preparation depends on the scan. An early scan may require a full bladder, while later abdominal scans usually do not. Wear clothing that allows access to your abdomen and bring previous reports and your estimated due date.
What does a pregnancy ultrasound report show?
The report records findings such as gestational age, fetal measurements, heartbeat, anatomy, placenta location, amniotic fluid, and fetal position when assessed. It does not prove that every condition is absent or guarantee a healthy pregnancy.
What symptoms after or during a scan require urgent help?
Seek urgent medical help for heavy vaginal bleeding, severe or one-sided abdominal pain, fainting, fluid leakage, fever, or reduced fetal movement after movements have been established. Contact your maternity team if you are unsure.
How do you choose and book the correct pregnancy ultrasound?
Use the exact scan name and gestational age on your referral or clinician’s request. Confirm the provider performs that scan, ask what preparation is required, check when the report will be available, and choose a centre with qualified staff and a clear pathway for discussing abnormal findings.